UEG's educational platform for gastroenterology education bringing recordings, courses, guidelines, and more together in one place.
Most popular content
Rate for better recommendations!
Your feedback helps us show you more of what you like and less of what you dislike!

Log in to continue.
This content is part of Gutflix. Log in with your myUEG account, or create one free, to watch it.
Not sure what you can access? Learn more about account types.
Panel discussion: Personalised therapy in locally advanced pancreatic cancer
Affiliations
1 Institut de cancérologie Gustave Roussy, Villejuif, France
2 Heidelberg University Hospital, Heidelberg, Germany
3 Trinity St James's Cancer Institute, Dublin, Ireland
4 Medizinische Klinik II, Muniche, Germany
5 Universitätsklinikum Ulm - Klinik für Innere Medizin I, Ulm, Germany
Log in to continue.
This content is part of Gutflix. Log in with your myUEG account, or create one free, to watch it.
Not sure what you can access? Learn more about account types.
Summary: Diabetes in GI disorders
Affiliations
1 Institute of Clinical Physiology, Pisa, Italy
2 Department of Internal Medicine II, Saarland University Medical Center, Homburg, Germany

Log in to continue.
This content is part of Gutflix. Log in with your myUEG account, or create one free, to watch it.
Not sure what you can access? Learn more about account types.
Standard of care or the IBD nurse curriculum
Affiliations
1 Danderyds sjukhus, Stockholm, Sweden

Log in to continue.
This content is part of Gutflix. Log in with your myUEG account, or create one free, to watch it.
Not sure what you can access? Learn more about account types.
Drug, dilation, or diet?
Affiliations
1 Università di Roma, Rome, Italy

Log in to continue.
This content is part of Gutflix. Log in with your myUEG account, or create one free, to watch it.
Not sure what you can access? Learn more about account types.
Oncology
Affiliations
1 University Medical Center Groningen, Groningen, Netherlands

Log in to continue.
This content is part of Gutflix. Log in with your myUEG account, or create one free, to watch it.
Not sure what you can access? Learn more about account types.
Alcoholic liver disease: A societal or individual disease?
Affiliations
1 Hospital Clínic, Barcelona, Spain
Log in to continue.
This content is part of Gutflix. Log in with your myUEG account, or create one free, to watch it.
Not sure what you can access? Learn more about account types.
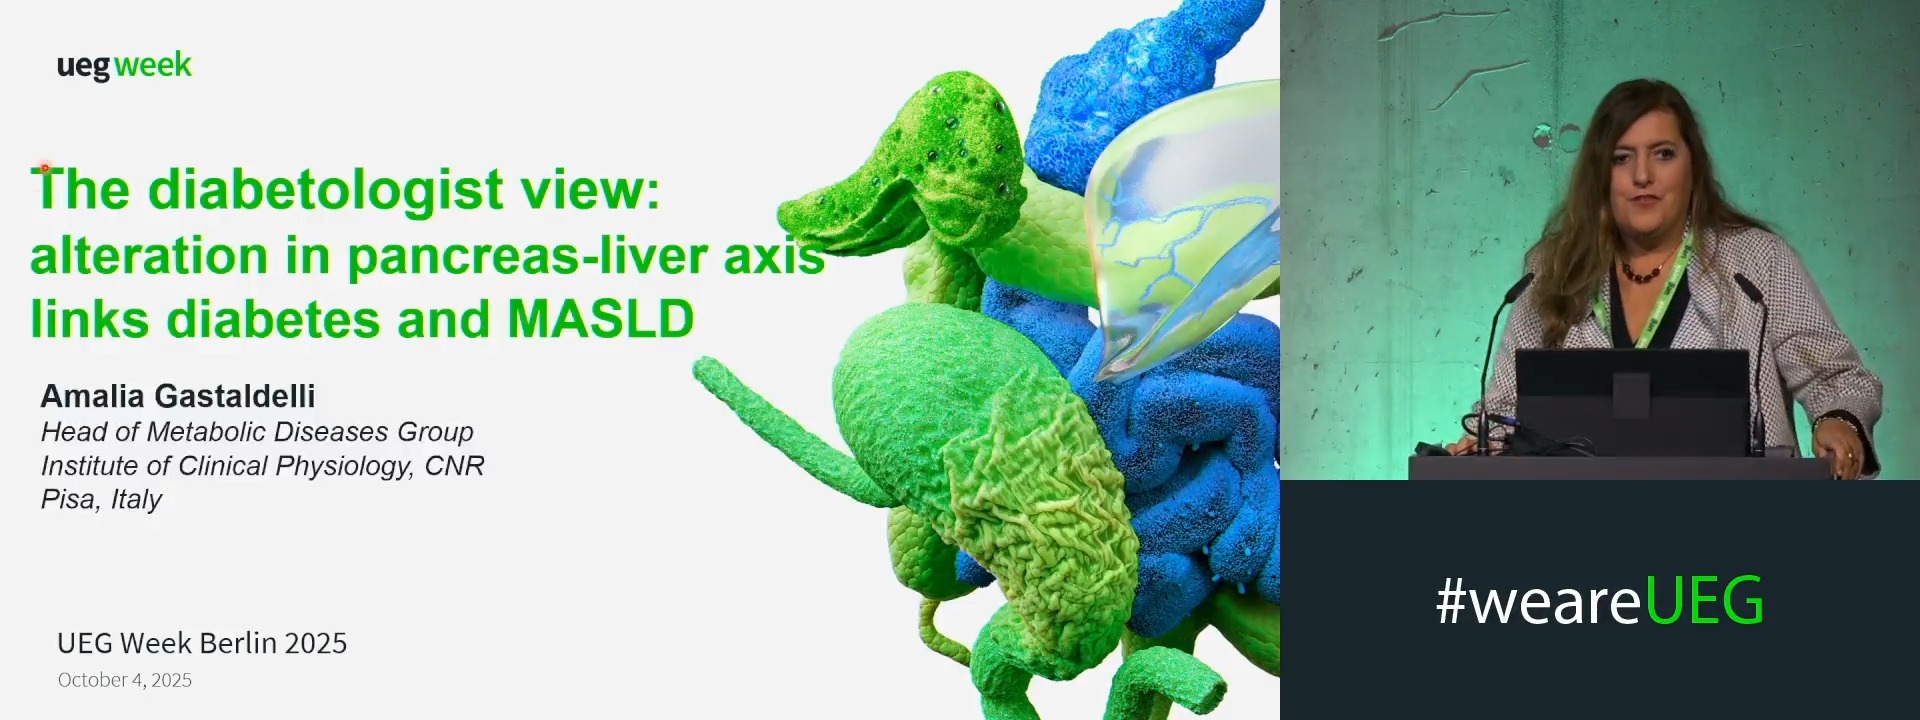
The diabetologist view: Alteration in pancreas-liver axis links diabetes and MASLD
Affiliations
1 Institute of Clinical Physiology, Pisa, Italy